Published in The Journal of Pediatrics: Changes in Suicidality Among Transgender Adolescents Following HT: An Extended Study
Key Study Takeaways
Drop in Endorsement: Among transgender and nonbinary (TNB) youth who endorsed suicidality at baseline, endorsement dropped by 65.2% at follow-up after starting hormone therapy (HT).
Reduction in Suicide Attempts: Reported recent suicide attempts dropped from 3.0% (13 patients) at baseline to 0.5% (2 patients) at follow-up: an 84.6% relative reduction.
Baseline Resilience: Most youth (78.7%) did not report suicidality at baseline, and 75.5% maintained zero suicidality throughout the observation window.
Effect Size: The reduction in suicidality remained statistically significant, with the effect size adjusting from large to medium as expected when scaling from a small sample to a larger cohort (N = 432).
Background: From the 2019 Pilot to the 2025 Extended Replication
In 2019, coming out of my dissertation (Allen et al., 2019), my co-authors and I published a small observational study (N = 47) examining changes in well-being and suicidality among transgender and non-binary (TNB) adolescents after the initiation of hormone therapy (HT). Given the wider replication crisis in the sciences (Ioannidis, 2005; Open Science Collaboration, 2015) and the decline effect (where initially large effects often shrink upon replication; see also my Blog on Purple Hat Therapies), larger, rigorously designed studies are necessary before drawing strong conclusions.
We completed a substantially expanded follow-up with 432 youth over a longer observation window (read the open-access publication). Although practical and ethical constraints in adolescent clinical research limit the feasibility of randomized controlled trials, accumulating data strengthens clinical confidence when consistent patterns emerge across independent cohorts.
Our 2025 study confirms our initial 2019 investigation: the reduction in suicidality following hormone therapy remains significant.
| Outcome Metric | Baseline (Pre-HT) | Follow-up (Post-HT) | Net Change |
|---|---|---|---|
| Endorsing Suicidality | 92 (21.3%) | 32 (7.4%) | -65.2% |
| Reported Recent Suicide Attempts | 13 (3.0%) | 2 (0.5%) | -84.6% |
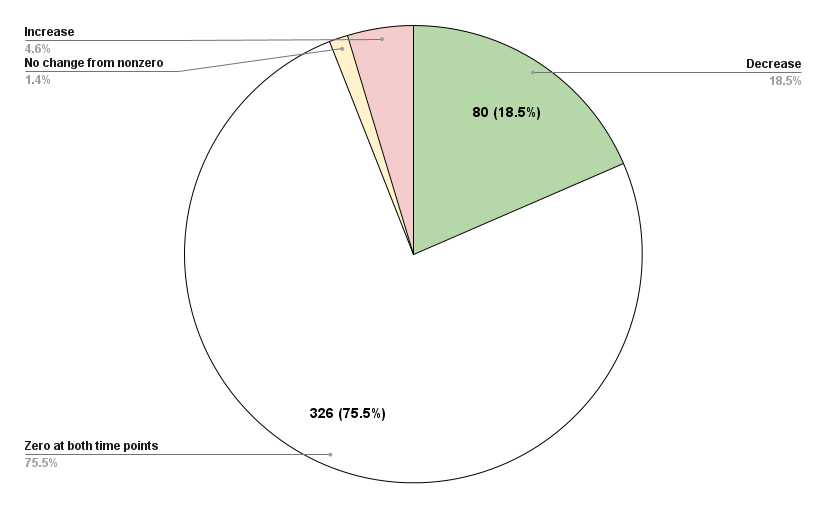
Most youth did not report suicidality at baseline; many were thriving in academic, social, and everyday settings. However, among the vulnerable subgroup endorsing suicidality prior to treatment:
Rates of endorsement fell by nearly two-thirds (65.2%).
Documented recent suicide attempts dropped by 84.6%.
New suicide attempts were rare during the follow-up window, even among patients entering care with a prior history of attempts.
While observational studies do not definitively establish causation, seeing similar improvements replicate across cohorts suggests this association reflects an underlying clinical reality. Sensitivity analyses further confirm that no standard analytical adjustment obscures the significant drop in suicidality endorsement (Allen et al., 2025b).
How Does This Study Fit into Broader Gender-Affirming Care Literature?
Evidence in clinical medicine accumulates incrementally. No single study settles a complex clinical question, and evaluating science requires examining study design, risk of bias, replication fidelity, and convergence across independent research teams (Nosek, 2025).
Across dozens of independent studies, transgender adolescents initiating medical interventions under clinical guidance reliably show measurable improvements across a spectrum of psychosocial outcomes (Turban, 2025; Budge et al., 2025).
Some degree of improvement observed in longitudinal cohorts may stem from general maturation, concurrent psychosocial support, positive expectation effects, or broader family changes. However, the consistency of outcomes across multiple independent datasets makes it unlikely that these trends are merely artifacts or random noise.
The Role of Evidence and Shared Decision-Making in Clinical Practice
Evidence-based practice is never solely about statistical tables. Clinical trial data cannot make a personal decision on behalf of a family or an individual.
Good clinical care integrates three pillars:
The best available empirical evidence.
Clinical expertise and developmental assessment.
The individual patient's values, priorities, and risk tolerance.
Different individuals weigh prospective risks, benefits, and uncertainties differently. Choosing a medical intervention carries considerations, but deciding not to intervene is neither neutral nor without risk.
What Is the Role of Mental Health Therapy in Gender Care?
Clarity regarding what psychotherapy can and cannot accomplish is essential:
What therapy cannot do: There is no credible empirical evidence that therapy can alter gender identity or resolve gender dysphoria by trying to change it.
What therapy does: Affirming gender therapy assists youth and families in exploring identity, clarifying values, examining emotional functioning, evaluating treatment options, and making informed choices.
Ethical gender care never involves prescribing an identity or pressuring a client toward a predetermined medical pathway. The clinician's role is to ensure decisions are informed, collaborative, and aligned with comprehensive standards of care.
For my other published research, visit my Publications page. If you are seeking clinical care, I offer online Gender Therapy and provide evaluations for Gender-Affirming Surgery Letters across all licensed and PSYPACT-participating states.
Study FAQs: Responses to Common Concerns
-
It’s a reasonable question. But it starts from the wrong assumptions.
The study wasn’t trying to isolate hormone therapy (HT) from everything else. It was designed to reflect how care actually works in gender clinics, where HT is delivered within a multidisciplinary model and standards of care (that includes mental-health support).
Therapy isn’t an optional “add-on.” Most youth who need support are already in therapy or are connected to community providers as part of standard care. That means there isn’t enough natural variation to “control for.” Nearly everyone gets some level of support, and the few who don’t differ for reasons unrelated to treatment (access, refusal, family dynamics, etc.). Those differences would mislead any attempt to compare “therapy vs. no therapy.”
It’d be like trying to study whether seatbelts make drivers safer in a group where almost everyone is already wearing one. There just isn’t enough difference to analyze, and the few who aren’t wearing a seatbelt aren’t randomly chosen: they differ in other important ways that matter more than the seatbelt itself.
The study does not answer the question: “What is the isolated effect of hormones alone?”
Instead, we answer: “What happens when young people receive hormone therapy as it is actually delivered in real clinical practice?”That makes the findings ecologically valid. They reflect real-world care, not an artificial experimental setup.
-
It’s true that control groups strengthen causal claims, but for this population, a true control group is practically and ethically impossible to create except in very rare circumstance (Schall, 2025). When researchers actually attempted this for puberty blockers (Mul et al., 2001), every family assigned to the untreated control group withdrew and sought care elsewhere. That outcome reflects the real constraint: families who want care will not remain in a “no-treatment” arm when other avenues exist.
Our study reflects treatment as usual (TAU), not an artificial experimental design in which access is withheld. In practice, a control group only becomes feasible when access to care has been restricted by law or policy and patients cannot obtain treatment elsewhere.
A comparison group would add value. But defining one is not straightforward. What would count as appropriate? Cisgender youth? Youth seeking but denied care? Youth with similar distress from unrelated causes? None are clean matches and some are not obtainable.
Even without a control group, the study provides meaningful, ecologically valid information about real clinical outcomes. The design doesn’t claim causation; it reports how suicidality changed over time in patients actually receiving care with a dataset that is rarely available and difficult to obtain.
-
Regression to the mean is always worth considering, but it doesn’t align with what we observed. Regression occurs when people start with extreme values and move toward average over time. But most youth in the study had zero suicidality at baseline and stayed at zero. You can’t regress from 0 to 0.
Among youth who did begin with non-zero suicidality, reductions were:
consistent across multiple years,
in the clinically expected direction, and
replicated with a larger, longer dataset (Allen et al., 2019).
Just as important: we saw no signal of group-level worsening. Some public narratives imply that regret or decline is common after starting HT; our data simply do not show that within the follow-up period.
To contextualize outcomes, our deterioration rate (4.6%) was comparable to or lower than deterioration rates seen in mental-health treatments more broadly (~5% to 10%). That doesn’t prove causation, of course, but it shows the pattern isn’t consistent with simple regression effects or broad decline.
Regression to the mean doesn’t fully explain the results we found.
-
You can read the full exchange here:
Letter to the Editor: The Ask Suicide-Screening Questions “Continuous Score”: An Unvalidated Endpoint
Our Reply: Analytic Treatment of the ASQ: Justification and Robustness of Findings
Both are pieces are technical, so here is a simplified breakdown of what the letter alleged and why those concerns don’t actually undermine the study.
Claim #1: We inappropriately turned the ASQ into a continuous score by summing yes/no items.
Reality: Summing binary items into an ordered severity score is routine in behavioral health research. Examples include:
ACE scores (count of 0/1 exposures)
Symptom-count indices in psychiatry (e.g., number of depressive symptoms present)
Risk screeners that sum yes/no indicators into a total score
The same logic applies to widely used measures like the PHQ-9: each item is ordinal and not evenly spaced, yet the total score is used as an indicator of severity. The purpose is to reflect more or less of the underlying construct: not to claim perfectly equal steps. Our use of the ASQ follows that same well-established approach, just as others have done with the ASQ (e.g., Kaurin et al., 2024).
Claim #2: Summing assumes the ASQ steps (0 → 4) are evenly spaced “units” of suicide risk.
Reality: That assumption appears nowhere in our paper, and our analysis doesn’t require it. The critique is aimed at a claim that was never made. We used the ASQ total for a straightforward: to examine changes in suicidality over time, which is stated plainly in the first three words of the title.
For that purpose, treating the ASQ total as an “ordered measure” is entirely appropriate. Ordered simply means that higher numbers reflect more suicidality; it does not require the steps to be evenly spaced. It’s similar to tracking a shift from “severe → moderate → mild” pain: the categories aren’t equally spaced, but the direction clearly matters.
As part of our analysis, we also checked the standard assumptions for this type of statistical analysis (including linearity), and they were satisfied: meaning the ASQ data behaved the way an our analysis (ANCOVA) requires.
Testing the Critique: Does this change what the data show?
The commentary argues that the ASQ levels (0, 1, 2, 3, 4) aren’t equally spaced. If one wanted to make the scoring “even,” the most conservative approach would be to remove the extreme item (item 4, recent suicide attempt) because it represents the biggest jump in severity. Removing item 4 would “smooth out” the scale.
We did that. And the results were unchanged. In this cohort, new suicide attempts were rare, and reductions in suicidality were common. No statistical critique can undermine this simple descriptive fact.
-
In theory, any retrospective study could miss events that happen entirely outside a health system. But in this setting, silent discontinuation within the observation window is extremely unlikely for several reasons:
Most health-system visits trigger a suicidality screening (not just gender clinic visits). In the hospital system, most routine clinical encounters automatically include a suicidality screening when one hasn’t been filled out recently. So a patient could be seen in nearly any clinic and still be captured in the data. The study did not rely on patients returning only to the gender clinic.
You cannot quietly stop HT without it showing up in the chart. Staying on treatment requires labs, follow-ups, refills, and dose adjustments: if someone stopped, those activities would stop too. Every chart was manually reviewed, and no discontinuation was found beyond the seven documented cases (4 identity shifts while still gender diverse, 2 unknown reasons, & 1 hair-loss concerns).
Every participant already had a follow-up suicidality assessment after starting HT. The study included only youth who had a baseline ASQ, and a second ASQ at least 3 months after starting HT. Even if some youth later disengaged from all care, the study still includes their last documented ASQ screening while they were receiving HT.
The data do not show a hidden pattern of deterioration. At follow-up: a) Suicidality significantly decreased on average, b) 75.5% had zero suicidality at both timepoints, c) only 4.6% worsened, & d) endorsement of recent suicide attempts dropped from 13 at baseline to 2 at follow-up. For a large number of youth to have secretly stopped HT and worsened dramatically without showing up in any system encounters would require a pattern that is not supported anywhere in the data.
Could someone deteriorate after leaving the entire medical system? Yes, just as they could continue to improve afterwards. That uncertainty exists in every retrospective study. But within the actual data, there is no evidence of widespread silent discontinuation or hidden worsening.
Bottom line: Suicidality was lower at the most recent observed visit. The structure of the health system makes silent discontinuation unlikely, and the observed pattern does not support that concern.
-
Because there was no reason. No one was excluded. If a patient received HT and had a follow-up ASQ at least three months later, they were included. There was no selective filtering, no recruitment process, and no study-driven dropout. A “CONSORT”-style flow chart is used when researchers are actively excluding or enrolling participants; that wasn’t part of this design.
The cohort is exactly what readers assume: every patient who received HT and had a follow-up ASQ.
-
Short answer: no.
The ASQ is built into hospital workflow. It is administered at most visits, or at least every 30 days, across departments. This makes missed assessments unlikely. Every patient in the study had a follow-up ASQ; that’s literally why they are appear in the data set. If a patient never completed a follow-up ASQ, they simply were not part of the before-after analysis.
Some might suggests that a patient could have stopped HT before their follow-up ASQ. If that happened, then it is extremely unlikely they would have been on a dose long enough or high enough to experience irreversible effects. And, even in such an imagined case, it would not undermine the findings. Any such hypothetical patients would not have been included in the analytic sample anyway: all patients youth did receive HT, did return for care, and did complete the ASQ again.
Manual chart review confirmed discontinuation was rare (7 of 432 patients). There is no evidence that a large number quietly stopped treatment or somehow bypassed suicidality screening.
Finally, the study replicated earlier findings using a much larger sample and nearly two years of average follow-up. There is no “missing dataset” that would meaningfully alter the observed pattern: after starting HT, suicidality was uncommon and new attempts were rare.
-
Probably not and there is more reason to suspect the opposite (at least for our specific study design).
By the time a patient sees a pediatric endocrinologist, they’ve already gone through psychological, and sometimes medical, evaluations. They’re essentially at the final step before starting hormone therapy. That situation usually brings relief and optimism. When people feel hopeful or expect good news, they tend to under-report distress, not exaggerate it. Think about the last time you were excited or anticipating good news: you probably didn’t focus on your worst feelings. This fits what the data show: most youth scored zero on the ASQ screening at baseline.
The ASQ is also just a routine safety check. It isn’t used to decide who gets treatment. So, there’s little incentive to “perform” distress. The pattern looks much more like deflated reports of distress at the start, not inflated ones. If anything, that makes the improvements seen after treatment even more noteworthy.
